



Search
- Page Path
- HOME > Search
Review Article
- Antibiotic Prophylaxis for Transrectal Prostate Biopsy
- Do Gyeong Lim, Seung Il Jung
- Urogenit Tract Infect 2026;21(2):47-55. Published online August 31, 2026
- DOI: https://doi.org/10.14777/uti.2652012.006
-
 Abstract
 PDF
 PubReader
 ePub
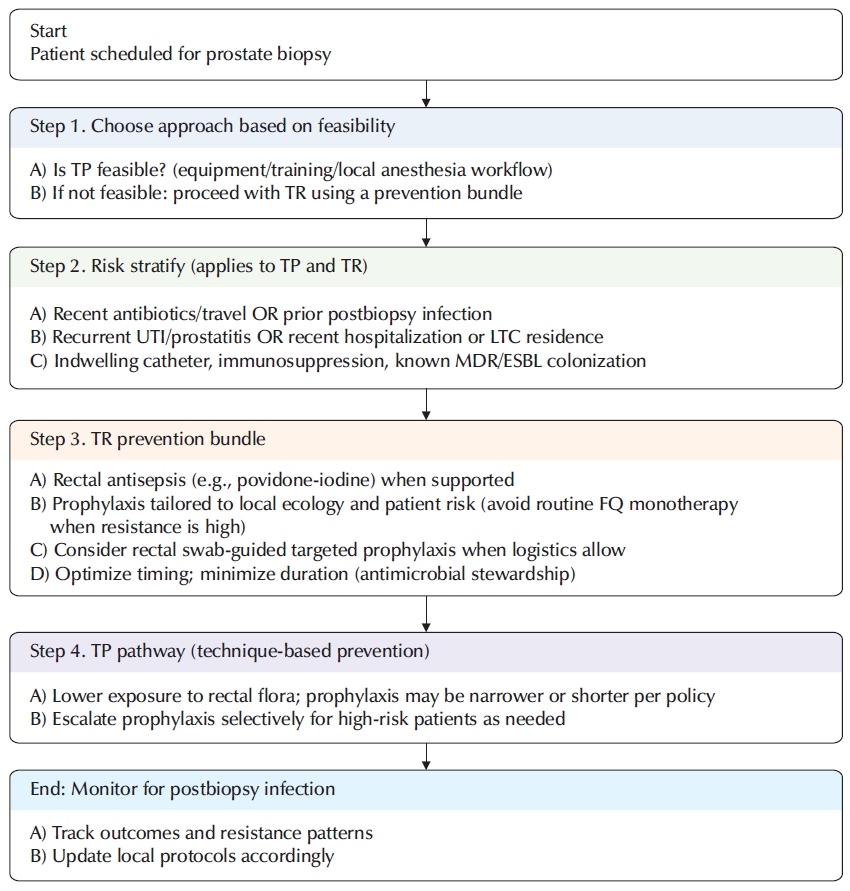
- Transrectal prostate biopsy (TRPB) is widely used for the diagnosis of prostate cancer but carries a clinically meaningful risk of infectious complications due to inoculation and translocation of rectal flora into the urinary tract and bloodstream. Antibiotic prophylaxis remains central to preventing febrile urinary tract infection and sepsis; however, increasing antimicrobial resistance—particularly fluoroquinolone-resistant Enterobacterales—has reduced the reliability of conventional empirical regimens in many regions. In this narrative review, we searched PubMed/MEDLINE, Embase, and Scopus for relevant literature published through February 2026 and synthesized current guideline positions and selected clinical evidence on prophylactic regimens, resistance-adapted regimen selection, and adjunctive measures for TRPB. Cumulative evidence indicates that the efficacy of fluoroquinolone monotherapy has significantly declined in regions with high-resistance prevalence. Alternative or augmented strategies (e.g., cephalosporin- or fosfomycin-based approaches) may reduce infectious complications in selected settings, although their performance appears context-dependent and may be accompanied by shifts in pathogen distribution. Rectal swab-guided targeted prophylaxis can individualize antibiotic selection; however, its effectiveness varies across studies because of methodological heterogeneity and imperfect prediction of clinical outcomes. Technique-based prevention, most notably transperineal biopsy, may reduce infectious risk while decreasing reliance on broad-spectrum prophylaxis. Taken together, infection prevention after prostate biopsy should be individualized according to local susceptibility patterns and patient-level risk while integrating antimicrobial stewardship and selecting adjunctive or technique-based measures when feasible.
- 1,939 View
- 22 Download

Original Article
- Efficacy of D-Mannose in the Management of Urinary Tract Infections: From Acute Treatment to Long-term Prophylaxis — A Systematic Review and Meta-analysis
- Jae Yong Jeong, Young Joon Moon, Dong Hyuk Kang, Hae Do Jung, Lawrence Kim, Joo Yong Lee
- Urogenit Tract Infect 2026;21(2):111-124. Published online August 31, 2026
- DOI: https://doi.org/10.14777/uti.2652010.005
-
Abstract
PDF
 Supplementary MaterialPubReaderePub
- Purpose
To evaluate the efficacy of D-mannose for preventing recurrent urinary tract infections (UTIs), including in kidney transplant recipients, and to clarify discrepancies between early openlabel and placebo-controlled trials. Materials and Methods: PubMed, Embase, CENTRAL (Cochrane Central Register of Controlled Trials), and Web of Science were searched from inception to February 2026. Randomized controlled trials (RCTs) comparing D-mannose with placebo, no treatment, antibiotics, or active controls were included. Risk of bias (RoB) was assessed using RoB 2, and certainty of evidence using GRADE (Grading of Recommendations, Assessment, Development, and Evaluations).
Results
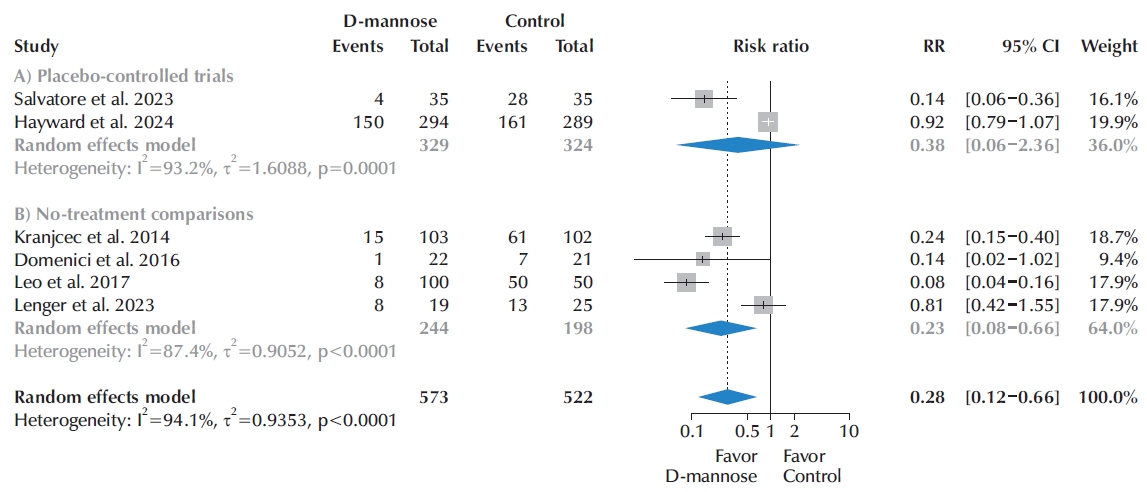
Eleven RCT reports involving 1,724 participants were included; 10 independent study populations involving 1,631 participants contributed to quantitative analyses. In placebo-controlled trials, D-mannose did not significantly reduce UTI recurrence or persistence versus placebo (risk ratio [RR], 0.38; 95% confidence interval [CI], 0.06–2.36). No-treatment comparisons showed reduced recurrence (RR, 0.23; 95% CI, 0.08–0.66), but were more vulnerable to expectation, performance, and detection biases. The exploratory combined estimate favored D-mannose (RR, 0.28; 95% CI, 0.12–0.66), but certainty was very low. Antibiotic comparisons were inconclusive (RR, 0.43; 95% CI, 0.18–1.05), whereas proanthocyanidins active-control comparisons favored D-mannose-containing regimens (RR, 0.57; 95% CI, 0.40–0.82), including data from kidney transplant recipients.
Conclusions
Current placebo-controlled evidence does not establish superiority of D-mannose over placebo. Apparent benefits were mainly driven by no-treatment comparisons with very low certainty. D-mannose remains biologically plausible but clinically uncertain; adequately powered, double-blind, placebo-controlled trials are needed before firm recommendations can be made.
- 2,639 View
- 30 Download
Review Article
- Mechanistic Insights Into Persistent Bacterial Cystitis as a Basis for Vaccine Development: A Narrative Review
- Karen Serrano-Arevalo, Manisha Naskar, Hae Woong Choi
- Urogenit Tract Infect 2024;19(3):60-72. Published online December 31, 2024
- DOI: https://doi.org/10.14777/uti.2448022011
-
Abstract
PDFPubReaderePub
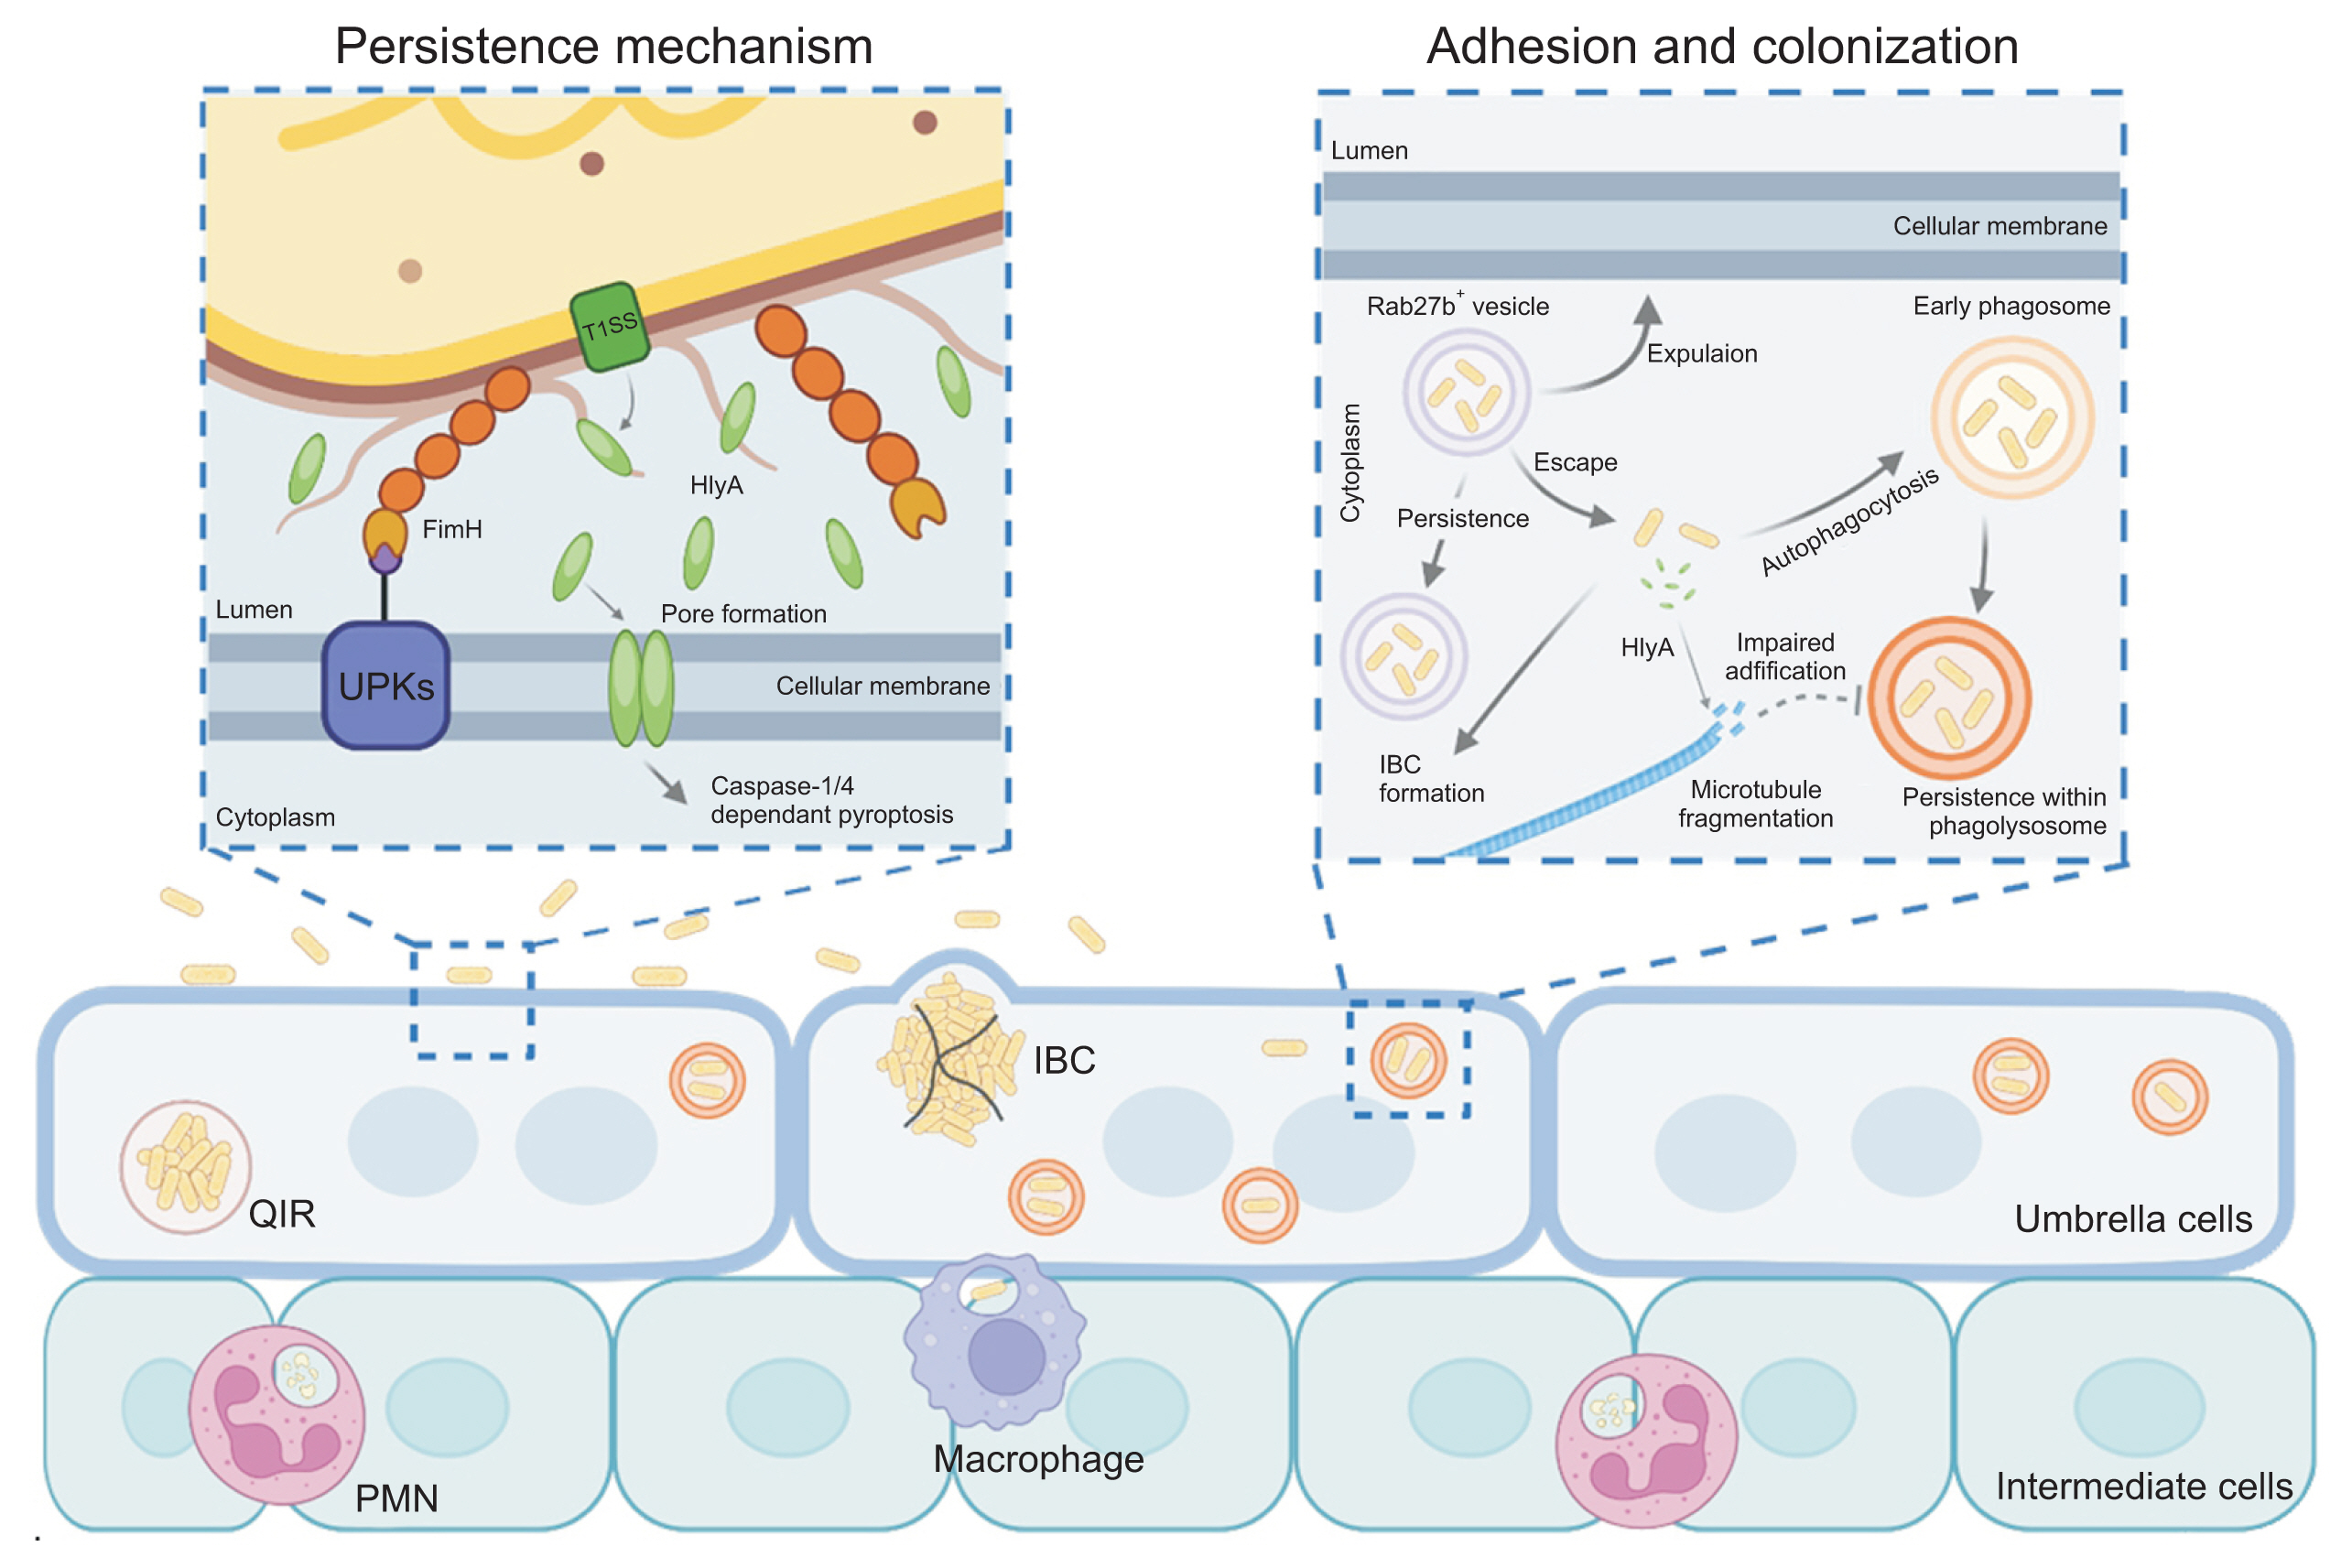
- Urinary tract infections (UTIs) are primarily caused by uropathogenic Escherichia coli (UPEC), which frequently lead to recurrent infections. These bacteria utilize several strategies to establish infection in the host; in particular, virulence factors such as fimbriae and α-hemolysin facilitate persistent infection, evade host immune responses, and minimize antibiotic exposure. To date, antibiotics have been the primary treatment for UTIs. However, an increasing emphasis has been placed on the need for UTI vaccines, with mucosal vaccine products now available in several countries. Additionally, vaccines targeting intracellular UPEC, utilizing adjuvants, are currently under development. Understanding the pathogenic mechanisms of uropathogens has enabled the development of new treatment approaches, paving the way for next-generation preventive and therapeutic methods that could effectively manage recurrent UTIs in the future.
-
Citations
Citations to this article as recorded by
- Mechanisms and clinical implications of bacterial persistence in recurrent urinary tract infections
Changil Choi, Dong Soo Kim, Jin Bong Choi, Taesoo Choi, Jeong Woo Lee
Investigative and Clinical Urology.2026; 67(2): 123. CrossRef - Antivirulence strategies targeting adhesion and biofilm formation in uropathogenic E. coli: Recent advances and clinical perspectives-review
Amina Bougouizi, Astri Dwyanti Tagueha, Lucia Nencioni, Cecilia Ambrosi, Daniela Scribano
Microbial Pathogenesis.2026; 219: 108757. CrossRef - Effects of UroVaxom on Urinary Tract Infection After Ureteroscopic Lithotripsy: A Multicenter Prospective Randomized Study
Sang Hee Lee, Kyung-Jin Oh, Ho Seok Chung, Cheol Kyu Oh, Myungchan Park, Hyun Tae Kim, Bum Soo Kim
Journal of Clinical Medicine.2026; 15(20): 7938. CrossRef - Bacterial biofilm – as a contributor to urinary tract infections
Zuzanna Trześniewska-Ofiara, Mariola Mendrycka, Agnieszka Woźniak-Kosek
Biuletyn Głównej Biblioteki Lekarskiej.2025; 58(384): 83. CrossRef
- Mechanisms and clinical implications of bacterial persistence in recurrent urinary tract infections
- 11,603 View
- 113 Download
- 4 Crossref
Original Article
- Impact of Microbial Infection on Sperm Parameters of Seminal Bacteria in Asymptomatic Subfertile Males
- Sae Byuk Chang, Tae Jin Kim, Tae Heon Kim, Seung-Ryeol Lee, Young Kwon Hong, Dong Soo Park, Sun-Mi Cho, Dong Hyeon Lee, Young Dong Yu
- Urogenit Tract Infect 2023;18(3):82-92. Published online December 31, 2023
- DOI: https://doi.org/10.14777/uti.2023.18.3.82
-
Abstract
PDFPubReaderePub
- Purpose: This study examined the effects of asymptomatic bacteriospermia on the semen quality of subfertile males. The types of bacteria and their antibiotic susceptibility were also analyzed.
Materials and Methods: Semen was collected and analyzed from 510 subfertile males. One hundred and seventy-nine males showed bacteriospermia, while 331 males did not. The bacterial species, sperm parameters, hormone levels, underlying disease, and lifestyle patterns were compared between the two study groups.
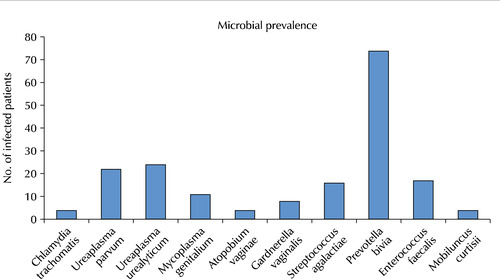
Results: The bacteriospermic males showed significantly higher rates of leukocytospermia (p=0.001) and deoxyribonucleic acid (DNA) fragmentation than the non-bacteriospermic males. Sperm motility was significantly lower in the bacteriospermic males than in non-bacteriospermic males. The most common seminal bacterial species were Prevotella bivia (P. bivia, 41.3%) and Ureaplasma urealyticum (U. urealyticum, 13.4%). U. parvum showed the highest recurrence rates (31.8%) three months after the initial antibiotic treatment. Regarding the sperm parameters of bacteriospermic males, the sperm concentration, total motility, progressive motility, leukocytospermia, and DNA fragmentation were improved significantly after the initial antibiotics treatment. Multivariate logistic regression analyses revealed P. bivia, U. urealyticum, and U. parvum to be associated with the decreased motility and increased DNA fragmentation of spermatozoa. P. bivia was also associated with a decreased sperm concentration (p=0.002) and vitality (p=0.013).
Conclusions: Bacteriospermia decreased the sperm concentration, motility, normal morphology, and vitality. P. bivia is the most commonly observed bacteria in subfertile males. Appropriate antibiotic therapy of seminal bacteria species had a strong positive impact on improving the semen parameters. -
Citations
Citations to this article as recorded by- Male Infertility in Burkina Faso: Analysis of Epidemiological, Diagnostic, and Therapeutic Profiles in a University Hospital
Clotaire Alexis Marie Kiemdiba Donega Yaméogo, Hassami Sawadogo, Brahima Kirakoya, Abdoul-Karim Pare, Soutongnoma Abdoul Euloge Kagambega, Adama Ouattara, Fasnewinde Aristide Kabore
Open Journal of Urology.2025; 15(11): 555. CrossRef
- Male Infertility in Burkina Faso: Analysis of Epidemiological, Diagnostic, and Therapeutic Profiles in a University Hospital
- 15,283 View
- 61 Download
- 1 Crossref
Reviews
- Prophylactic Antimicrobial Therapy and Antimicrobial Stewardship in Urologic Surgery
- Hee Jo Yang
- Urogenit Tract Infect 2023;18(1):8-14. Published online April 30, 2023
- DOI: https://doi.org/10.14777/uti.2023.18.1.8
-
Abstract
PDFPubReaderePub
- Postoperative infectious complications are a worrying problem for surgeons. Urological surgery has a higher risk of postoperative urinary tract infection than other surgeries because of the common use of various types of catheters. Due to the recent increase in antibiotic resistance, antimicrobial stewardship recommends using appropriate antibiotics for a suitable period. It is generally advocated that prescribing antibiotics in the absence of infection is equivalent to the inappropriate use of antibiotics. Based on numerous studies reported by several academic societies, appropriate use of antibiotics before surgery has been suggested. It was confirmed that using antibiotics according to these guidelines reduces the use of antibiotics without increasing the incidence of postoperative infectious complications. Furthermore, endourological surgery reports have proved the efficacy of antibiotics given once before surgery. Differences in antibiotic resistance by region must be taken into consideration when selecting the appropriate antibiotic type.
-
Citations
Citations to this article as recorded by- Safety of Omitting Antimicrobial Prophylaxis in Laparoscopic Donor Nephrectomy: A Prospective Observational Study
Shivam Mishra, Kunal Vinayak, Rahul Bhan, Venkatesh Singhal, Abhinandan Mukhopadhyay, Varun Mittal
Indian Journal of Transplantation.2026; 20(1): 43. CrossRef - Effects of UroVaxom on Urinary Tract Infection After Ureteroscopic Lithotripsy: A Multicenter Prospective Randomized Study
Sang Hee Lee, Kyung-Jin Oh, Ho Seok Chung, Cheol Kyu Oh, Myungchan Park, Hyun Tae Kim, Bum Soo Kim
Journal of Clinical Medicine.2026; 15(20): 7938. CrossRef
- Safety of Omitting Antimicrobial Prophylaxis in Laparoscopic Donor Nephrectomy: A Prospective Observational Study
- 12,849 View
- 137 Download
- 2 Crossref
- Virus in the Urine of Healthy People and Patients with Infectious Diseases
- Sunho Park, Eui Tae Kim, Jung-Sik Huh
- Urogenit Tract Infect 2021;16(2):44-48. Published online August 31, 2021
- DOI: https://doi.org/10.14777/uti.2021.16.2.44
-
Abstract
PDFPubReaderePub
- There has been a sustained effort to overcome the multiple infectious diseases that confront humankind. Urinary tract infections (UTIs) are most commonly caused by bacterial pathogens, primarily Escherichia coli. However, UTIs by viral pathogens have not been significantly reported. The human urinary tract, both in the healthy and diseased states, is home to many viruses despite the traditional belief that urine is sterile in healthy individuals. The most common viral pathogens found in the urinary tract are the human polyomavirus (BK virus), adenovirus, cytomegalovirus, and herpes simplex virus type-1 and type-2. Research should continue to investigate whether these viruses cause clinical infections or are mere colonizers of the urinary tract. Keywords: Urinary tract
-
Citations
Citations to this article as recorded by- Microfluidic-Based Molecular Diagnostics for Pathogen Detection in Urine Samples for Resource-Limited Settings: A Review
E. Alperay Tarim, Natish Kumar, Michael Mauk, Mohamed El-Tholoth
ACS Sensors.2026;[Epub] CrossRef - Unveiling indicator, enteric, and respiratory viruses in aircraft lavatory wastewater using adsorption-extraction and Nanotrap® Microbiome A Particles workflows
Warish Ahmed, Wendy J.M. Smith, Ananda Tiwari, Aaron Bivins, Stuart L. Simpson
Science of The Total Environment.2023; 896: 165007. CrossRef
- Microfluidic-Based Molecular Diagnostics for Pathogen Detection in Urine Samples for Resource-Limited Settings: A Review
- 18,420 View
- 65 Download
- 2 Crossref
 First
 Prev



